Hisanori Yuminaga, Katsuma Yamada, Masaru Ogiri (2021). Changes in Electroencephalography Signals During Massage. In: Advances in Human Aspects of Healthcare. AHFE Open Access, vol. 13. https://doi.org/10.54941/ahfe100488
This study aimed to analyze the effect of massage on mental mechanisms by using electroencephalography (EEG) before, during, and after massage. The patient was placed in a supine position and received a massage from both an expert physical therapist, with 20 years experiences, and a person with no experience in therapeutic massage. EEG was recorded before, during, and after the massage. The portion of the body given the massage was only the left-side plantar arch, and the massage method was finger pressure applied by the thumb. The massage given by the expert evident alpha waves after massage. In contrast, the massage given by the inexperienced person did not induce any alpha changes. In this study, a massage from an inexperienced person did not change alpha activity before, during, or after the massage. Accordingly, the appearance of an alpha wave after massage is thought to correspond to the level of arousal of the patient gradually decreasing after massage—an indication that the patient had had a comfortable experience. In this study, it is suggested that a massage given by an expert physical therapist promotes emotional stability.
Physiological and mental stress and high levels of body tension are often sources of difficulty for people in modern society. Occupational-related mental stress can contribute to general mental stress, which can produce an array of physical symptoms. A significant social problem in today’s world is that people can find it difficult to develop and maintain a social life because of this mental stress. Mental stress can not only contribute to mental disorders, but also various physical symptoms including shoulder pain and lower back pain. High levels of mental stress can cause sympathetic nerve symptoms and high levels of muscle tension, which are apparent in sympathetic nerve activity.
The sympathetic nervous system is one division of the autonomic nervous system—the other being the parasympathetic nervous system—and is responsible for initiating and maintaining homeostatic responses. Sympathetic nerves mediate the hormonal stress response commonly known as the fight or flight response (Mountcastle, 1980). The fight or flight response is induced by sympathetic nerve stimulation of the adrenal system, whereby preganglionic sympathetic fibers that terminate in the adrenal glands cause them to secrete adrenaline and, to a lesser extent, noradrenaline. This response primarily affects the cardiovascular system by directly mediating impulses transmitted through the sympathetic nervous system and by indirectly mediating catecholamines secreted by the adrenal medulla (Mountcastle, 1980). Sympathetic nerves also cause a range of physical responses including pupil dilation, increased heart rate, increased heart contraction, constriction of blood vessels, and increased blood pressure (Mountcastle, 1980). Muscle tension caused by sympathetic nerves causes tension myositis/myoneural syndrome (TMS), coined by John E Sarno. He described TMS as a condition characterized by psychogenically induced musculoskeletal and nerve symptoms (Sarno,1981). According to Sarno, TMS is a condition in which unconscious emotional issues initiate a process that causes physical pain and other symptoms. He suggests that the unconscious mind uses the autonomic nervous system to decrease blood flow to muscles, nerves, or tendons, which results in oxygen deprivation and is experienced as pain in affected tissues (Sarno,1981). Sarno states that the underlying cause of pain is the mind’s defense mechanism, which is an unconscious mechanism used to cope with mental stress and emotions (Sarno,1981).
Many people suffer with lower back pain, shoulder pain, and neck pain. It is a problem in modern society, which people seek treatment for at a significant financial cost. These symptoms relate to not only physical stress, but to mental stress as well. Physical symptoms caused by mental stress are psychosomatic, and one of the most common psychosomatic symptoms is pain. Pain is defined as “an unpleasant sensory and emotional experience associated with actual or potential tissue damage, or described in terms of such damage” (Mountcastle, 1980). Pain is subjective, but nonetheless it can lead to physical problems, including bone damage, soft tissue damage, and nerve damage. Emotional conditions can also contribute to pain. In particular, social stresses correlate with pain, which are the primary factor that hinders efficiency in physical movement and contributes to emotional instabilty.
The main objective of physical therapists is to relieve pain and thus provide physical and mental relaxation. Massage is one therapeutic technique used by physical therapists to decrease pain, and it is the manipulation of superficial and deep layers of muscle and connective tissue using various techniques (Kuriyama and Goto, 2008). While often used recreationally, massage used therapeutically can enhance function, aid in the healing process, decrease muscle reflex activity, inhibit motor neuron excitability, and promote relaxation and wellbeing (Kuriyama and Goto, 2008). Massage involves manually or mechanically manipulating the body with pressure, tension, motion, or vibration. Target tissues may include muscles, tendons, ligaments, fascia, skin, joints, other connective tissue, lymphatic vessels, or organs of the gastrointestinal system(Kuriyama and Goto, 2008).Specific treatments incorporate these techniques into their regimen, such as medical massage, lymphatic drainage massage, and myofascial release massage. Reviewed medical research has shown that the benefits of massage include pain relief, reduced blood pressure, reduced heart rate, and reduction in anxiety (Kuriyama and Goto, 2008). Theoretical suggestions for the therapeutic mechanism of massage include blocking nociception, activating the parasympathetic nervous system (which may stimulate the release of endorphins and serotonin), preventing fibrosis or scar tissue, increasing lymph flow, improving sleep, promoting relaxation, and alleviating negative emotions. Overall, massage therapy has substantial physical and mental benefits (Kuriyama and Goto, 2008). However, these effects lack the support of well-designed clinical studies. Massage contributes to central nervous system neuromuscular excitability, yet, the physiological effects caused by massage are still not clear. In this study, we examined an electroencephalogram (EEG) before, during, and after massage delivered by an expert and an inexperienced person.
EXPERIMENTAL TRIALPARTICIPANTS Participants
The participant classified as a massage expert had 20 years of experience versus the participant classified as inexperienced. The massage recipient underwent assessment before the massage, during the massage, and after the massage (1 min, 2 min, and 3 min). One patient received massage (21 years of age; height: 165 cm; weight: 60 kg). All participants were informed of the purpose of the study, and provided written consent prior to enrolment.
Method
Electroencephalograms were recorded from the back of the head from the patient before, during, and 1 and 2 min after massage (see Figure 1). The patient received massage while in the supine position, with his eyes closed. In order to standardize the EEG trial, the patient was asked to mentally calculate arithmetic for 30 s, after which he watched scenes from a movie. Baseline brain wave data was collected and confirmed prior to collecting EEG measurements. Experimental massage was delivered to the patient before (B), during (D), and immediately after (IA; 1 min, 2 min, and 3 min). In order to avoid compromising the EEG, the room within which they were measured was quiet and well lit with an ambient temperature of 26 ℃.
Careful attention was paid to the set-up so that weak EEG signals were not affected. The expert and inexperienced masseuses delivered slow and rhythmic massage (1 to 0.5 Hz) to the left side plantar using the participant’s thumb. This technique was used so that the body was not disturbed.
Figure 1 The patient position while experimentation.
Electroencephalogram measurement Electroencephalogram data was collected with the Muse Brain system (Digital Medic. Co. Ltd). This system uses a brain sensor headband, which detects and measures spontaneous oscillations in neuronal activity. Brain activity and frequencies vary according to one’s state of mind.
The brain generates electrical frequencies that are detected using EEG sensors along the surface of the skull. The Muse Brain system detects three main brain waves at any given time. Each brain wave band occurs with different proportions and the Muse Brain system measures changes in those proportions, which are reflective of altered states of mind. Theta waves are associated with sleep, very deep relaxation, and visualization. Alpha waves occur when relaxed and calm. Beta waves occur when thinking actively or problem solving. The Muse Brain system is used to visualize stress in real time through brain responses using sensors to detect and measure brain activity. This activity is converted into information and stored on a computer where it is transcribed into visual form, allowing brain performance to be assessed in real time. The Muse Brain system is the only brain sensor headband that is adjustable and designed to fit most head sizes. The system was ergonomically designed for comfort, fit, and strong signal quality. The system is placed around the back of the head to measure alpha waves and behind both ears as a reference (see Figure 2, 3).
Figure 2 Muse brain system (Digital Medic. Co. Ltd).
Figure 3 EEG setting.
Data analysis Measured brain activity was comprised of the total intensity of all theta wave, alpha wave, and beta wave frequency bands. We analyzed alpha waves as an indicator of relaxation and divided the total intensity of all frequency bands by the total intensity of alpha waves. Total content was calculated by the percentage of alpha waves relative to the alpha wave value prior to the massage, which was set at 100%. These values were compared between the expert and inexperienced masseuse.
Furthermore, the alpha wave data collected during the massage period from both the expert and inexperienced masseuse was temporally normalized and smoothed from 0% to 100% (TRAIAS, SAKAI Co., Ltd).
RESULTS
The following outlines the alpha wave content by percentage.
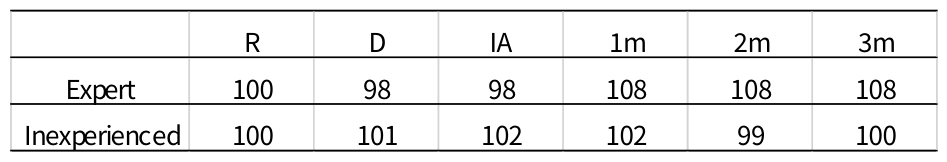
Expert masseuse Relative to the value before the task (i.e., 100%), alpha waves comprised 98% of the waveforms during massage. This increased to 108% immediately after the massage, which was maintained throughout all time points (1, 2, and post-3 min). Compared to pre-massage measurements, alpha wave content during massage was lower, but increased immediately after massage (see Table 1, Figure 4).
Inexperienced masseuse Relative to the value before the task (i.e., 100%), alpha waves comprised 101% of the waveforms during massage. This increased to 102% immediately after the massage (1 min post-massage), dropped to 99% (2 min post-massage), and returned to 100% (3 min post-massage). Alpha wave content during and post-massage period was slightly higher compared to the wave content before massage (see Table 1, Figure 4).
Table 1. Graph of Alpha wave relative value.
2m: 2 minutes after massage, 3m: 3 minutes after massage
[V]
Expert
系列1 Expert
100
系列2 Inexperienced
98
96
Inexperienced
108
94
92
1 2 3 4 5 6
106
104
102
系列1
100
系列2
98
96
94
92
1 2 3 4 5 6
R DM IA 1m 2m 3m R: Rest, DM: During massage, IA: Immediately After, 1m: 1 minutes after massage,
2m: 2 minutes after massage, 3m: 3 minutes after massage
Figure 4 Graph of Alpha wave relative value.
Smoothing of alpha waves Expert masseuse: There was a loose alpha wave pattern prior to the massage, which intensified during the massage. It showed a loose pattern again 1 min to 3 min post-massage.
Inexperienced masseuse: A pattern similar to that induced by the expert masseuse was revealed throughout all time points; however, there was a difference in the intensity between the expert and inexperienced masseuse (see Figure 5).
[V] R
D
IA
1m
2m
3m 0 100(%)
0 100(%) Expert Inexperienced
R: Rest, DM: During massage, IA: Immediately After, 1m: 1 minutes after massage, 2m: 2 minutes after massage, 3m: 3 minutes after massage
Figure 5 Smoothing of Alpha wave.
Interview We conducted an interview with the patient who received the massage. He said that when the expert performed the massage it was very pleasant and that he became sleepy. On the other hand, he had said that when the inexperienced masseuse performed the massage that it was painful and unpleasant.
DISCUSSION
An EEG is a recording of electrical activity from areas along the scalp. Electroencephalograms measure voltage fluctuations resulting from ionic current flows within the neurons of the brain. In clinical contexts, EEG refers to the recording of the brain’s spontaneous electrical activity over a short period, usually 20–40 min, recorded from multiple electrodes placed on the scalp. Electroencephalograms record the type of neural oscillations. Neurons are electrically charged and the electrical charge of the brain is maintained through membrane transport proteins that pump ions across the neuronal membrane. Neurons are constantly exchanging ions with the extracellular environment in order to maintain resting membrane potential and to propagate action potentials.
Electroencephalogram signals fluctuate between 1–60 Hz (i.e., 10–100 μV). The main consequence of an action potential is the induction of a postsynaptic potential. These occur in all neurons of the brain, including pyramidal neurons. The cell body of pyramidal neurons has longer dendrites, which are distributed throughout the cortex and deeper layers (i.e., layer five). This composition creates a dipole between superficial and deeper layers. In theory, depolarization of pyramidal cell bodies may cause the surface of the soma to be negatively charged. This negative potential could induce an electrical field by an electric current received by the cell body from the tip of a dendrite. Electroencephalogram signals are a main reflection of an electrical change caused by pyramidal neuron activity. The rhythm of EEG signals are mediated by thalamic neuronal activity, which are affected by the midbrain (i.e., brainstem reticular activating formation), creating both excitatory and inhibitory postsynaptic potentials (Lodder and Putten, 2014).
Many electrodes are used to create an EEG recording and the montage primarily used is the international 10–20 system. The functional EEG is comprised of background and unexpected EEG. The background EEG is a basic fluctuation wave induced by neuronal activity on subliminal electrodes. When pyramidal neurons of the cerebral cortex are functioning normally, the EEG signal displays an alpha rhythm at rest and a beta rhythm during activity. An abnormal wave is characterized by a slow wave, which becomes a burst wave (a transient change in the rhythm of the background wave). Under normal conditions, an EEG displays pyramidal neuron activity of the cerebral cortex, the brain’s surface. This activity is initiated by brainstem and cortical projections, apparent in high voltage slow and burst waves induced by deeper abnormal activity. High voltage waves are evidence of dysfunctional, malfunctioning, and immature neuronal activity (Lodder and Putten, 2014).
An EEG is described in terms of rhythmic and transient activity. Brain activity is categorized as alpha, theta, delta, or beta wave. Alpha waves are considered basic waves with a frequency ranging from 8 Hz to 14 Hz (approximately 10 Hz). It has been shown that posterior and parietal-temporal lobe alpha waves are higher in amplitude on the dominant side. These emerge when the eyes are closed and during relaxation, and attenuate when the eyes are open and during mental exertion. Beta waves occur in a frequency range from 15 Hz to approximately 30 Hz. Beta waves occur bilaterally with symmetrical distribution, predominantly in the frontal lobe. Beta wave activity is closely linked to motor behavior and is generally attenuated during active movement. It is low in amplitude with multiple and varying frequencies and associated with active, busy, or anxious thinking and concentration. Beta waves occur along the scalp in the anterior and temporal lobes. Theta waves are low in amplitude and with a frequency range of 4 Hz to 8 Hz. These are evident during drowsiness in adults or arousal in children and are displayed in the temporal lobes. Delta waves occur in a frequency range of 0 Hz to 3 Hz. These waves tend to be the slowest but the highest in amplitude. Delta waves are normally evident in non-rapid eye movement slow wave sleep in babies and adults (Kandel and Schwartz, 2000).
Our results show that the percentage of alpha waves occurring during and immediately after massage decreased in comparison to the percentage occurring before massage. In the expert massage condition, the percentage of alpha waves significantly increased from 1 min to 3 min after massage compared to the percentage before massage. On the other hand, in the inexperienced condition, the percentage of alpha waves during and just after massage increased slightly and significantly in comparison to before massage and from 1 min to 3 min after massage. Our original hypothesis was that the alpha wave percentage would increase during massage by an expert masseuse. However, the alpha wave percentage in the expert condition did not increase from massage to post-massage, but rather thereafter. For this reason it is suggested that arousal levels increase by the patient attending to the plantar area being massaged. Furthermore, we suggest that the percentage of alpha waves that increased in the expert condition was due to the positive stimuli experienced by the patient from 1 min to 3 min after massage. On the other hand, we suggest that in the inexperienced condition, arousal level increased while alpha wave percentage did not in order for the patient to recognize unpleasant stimuli. However, the alpha wave percentage did slightly increase during and just after massage in both the expert and inexperienced conditions. Thus, we suggest that the patient gave more attention to the expert massage than to the massage delivered by the inexperienced masseuse.
Pleasant and unpleasant attributions are made in a phylogenetically primitive part of the brain, the limbic system. The limbic system is a set of brain structures that forms the inner border of the cortex. The components that are located in the cerebral cortex have fewer layers than the classic six-layered neocortex, referred to as allocortex or archicortex. It is composed of the limbic lobe (parahippocampal, cingulate, subcallosal gyrus, hippocampus, and dentate gyrus) and other deep-lying structures (hippocampus, amygdala, mammillary body, habenula, anterior thalamic nuclei, and olfactory bulbs). The limbic system supports a variety of functions, including emotion, behavior, motivation, long-term memory, and olfaction. The limbic system is modulated by the neocortex, which contains plentiful connections with the limbic system. Human control of emotions plays an important role in society (Kandel and Schwartz, 2000).
As a result, massage delivered by experts induces pleasant stimuli compared to massage delivered by inexperienced individuals. It is suggested that massage delivered by experts could contribute to relaxation and, as a consequence, a more stable mental state. As far as we know, there is no other published research regarding EEG during massage. Potential reasons for this may be that EEG recording is very difficult to carry out with weak signals, and that EEG apparatus is expensive. Further, conducting such studies requires that study rooms are appropriately set-up in order to record EEG. Despite the fact that massage therapists have confirmed the effects of massage, this has not been confirmed scientifically. In this study, it was useful that neural activity was confirmed in real time before, during, and after massage. This allowed us to analyze the clinical effect of massage across these time points.
Alpha waves are indicative of mental stability and physical relaxation. When receiving massage from an expert, the patient said that they were “very comfortable.” However, the percentage of alpha waves did not increase during the expert’s massage; rather, it decreased. We suggest that the patient’s level of arousal increased in order to pay attention to the sole of the foot during massage, allowing for the maintenance of this pleasant stimulus. We suggest that the percentage of alpha waves increased after the expert’s massage in order for the patient to receive pleasant stimuli. Therefore, we suggest that the percentage of alpha waves did not increase when the patient felt unpleasant stimuli during the massage delivered by the inexperienced masseuse (Kandel and Schwartz, 2000).
Gamma-alpha-butyric acid (GABA) and serotonin are neurotransmitters released during periods of mental and physical relaxation (Lodder, Shaun, Askamp, Putten, Zhan, 2014). When the percentage of alpha waves increases, GABA and serotonin are released by neurons in greater amounts. Serotonin neurons predominate in the nine raphe nuclei, which are bilaterally located on the brainstem. Each raphe nucleus projects to various areas of the brain. The caudal raphe nuclei of the medulla oblongata control spine-related pain. The ventral raphe nuclei of the pons and midbrain have a wide range of axonal connections and control most brain areas, similar to the locus coeruleus. The raphe nuclei release neurotransmitters predominantly during arousal. A specific raphe serotonin neuron mediates the brainstem reticular activating formation, which is involved in arousal and secretes a sleep hormone. Neuronal release of serotonin also increases during concentration and meditation. Furthermore, it is well documented that serotonin neurons are activated during rhythmic movement, such as walking and massage (Lodder, Shaun, Askamp, Putten, Zhan, 2014).
CONCLUSIONS
From this study, we can conclude that rhythmical pleasant stimuli, such as massage delivered by an expert masseuse, induces the release of serotonin. In comparison to massage delivered by an inexperienced masseuse, this release increases the arousal of the patient, but not the percentage of alpha waves, during massage. The inhibitory neurotransmitter GABA would diminish any mentally excited state. As with serotonin, GABA has wide distribution and is involved in sleep and arousal. It is our conclusion that a decrease in alpha wave percentage caused the patient’s arousal to increase with the rhythmic stimulus provided during the expert’s massage. We suggest that it induced relaxation via the repeated presentation of a pleasant stimulus at 1 min to 3 min after the expert’s massage, resulting in mental stability, and decreased arousal. In this study, the release of neurotransmitters during a massage is different when delivered by an expert masseuse versus an inexperienced one.
REFERENCES
Kandel, E.R., James, H.Schwartz, J.V., Jessell, T.M., (2000), “ Principles of Neural Science Fourth edition”,McGraw-Hill Kim, S.C., Myoung Hee Lee,M.H., Jang, C, Kwon, J.W., Park, J.W., “ The effect of Alpha Rhythm Sleep on EEG Activity and Individuals’ Attention” J Phys Ther Sci. 1515–1518 Kuriyama, S., Goto, S., Uchida, M. (2008), “ Athletic Massage by DVD”, Nankodo.Co Ltd, 2008 Lodder, Shaun.S., Askamp,J., Putten, M,J,A,M., Zhan,W,.(2014),” Editor Computer-Assisted Interpretation of EEG Background
Pattern: A clinical Evaluation”,: PLoS ONE 9(1) Mountcastle, V.B. (1980), “Medicla Physiology Fourteenth edition”, The C.V.Mosby Company .pp. 893-922. Sarno JE. (1981), “Etiology of neck and back pain. An automatic myoneuralgia?”,: J.Nerv Ment Dis.169 (1), pp55-59.
LISTED IN THE AHFE DIGITAL BOOKSTORE CATALOGUE
Explore the complete digital volume
Advances in Human Aspects of Healthcare
Read this individual research paper free through the original publisher, or explore the full digital proceedings book.
ISBN 978-1-4951-2093-0
Explore this ISBN in the AHFE Bookstore ↗Listed in the July 2026 bookstore catalogue; search by ISBN to confirm current availability · Digital book purchase optional