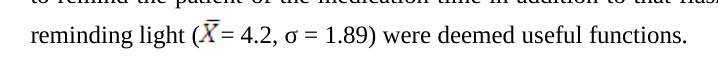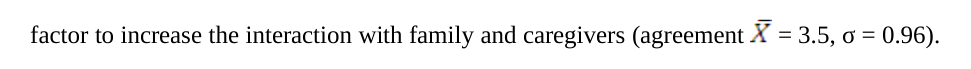Fei-Hui Huang (2021). The Needs of Smart Medication Reminder for Elderly s. In: Advances in Human Aspects of Healthcare. AHFE Open Access, vol. 13. https://doi.org/10.54941/ahfe100523
The increasing burden of chronic illness is currently a significant challenge due to the aging of the global population. For most people who suffer from chronic illnesses, lifelong treatment is needed for their health management. This study is focused on the needs of elderly people with chronic conditions who require lifelong treatment for disease management in taking medications as prescribed. A face-to-face survey and a multiple case study were conducted to elicit the reasons why elderly s use pill box and to determine the effectiveness of the smart medication reminder system. The results indicated that 60% patients need a tool for assistance in taking their medication as prescribed. The experimental results showed that the smart medications reminder may effectively assist users in taking their medications as prescribed. The patients’ needs for the smart mediation reminder include reminder design, mobile medication reminder, ease of use, flexible design, and Modular Design. By using the smart medication reminder, the pressure of taking medications as prescribed may be relieved for the most elderly users. Furthermore, economic, social support, and elder care subsidies are the important factors for patient welfare.
By the year 2020, more than 1 billion people will be older than 60. Taiwan has one of the world’s most rapidly aging societies due to the rapid expansion of the elderly population and the low birth rate, which was only 0.9 in 2010. Taiwan was classified as having an aging society in 1993 due to the proportion of elderly residents comprising 7% of the total population and will be classified as an aged society by 2018. According to the Ministry of Interior data, 11.15% of the total Taiwan population was older than 65 years in 2012, and the aging index was 76.21%. The aging of the population has been projected to approach 24.8% in 2036. Furthermore, the elderly represent the largest and most active sector of health care and medication consumers (Steinman & Hanlon, 2010). A report presented by the National Health Insurance in Taiwan has shown that as much as 89% of the population aged 65 years and older is affected by at least one chronic illness and that more than 56% of all health care expenditures are related to the treatment of chronic conditions.
For most people who suffer from chronic illnesses, lifelong treatment is needed for their health management. Failure to take their medications regularly as prescribed can be dangerous and even life threatening. Many of these elderly people will require long-term care, in the form of home- or community-based health care or nursing home care and will require expanded health care services and facilities for assistance with normal daily activities. Because many elderly residents prefer to remain in their private residences for as long as possible, assistance methods are required to increase their autonomy and thus enable them to self-manage their lives safely and at reasonable costs. In addition, telehealthcare has the potential to enable the elderly to remain in a familiar environment close to family and friends and to increase well-being. Such a measure is designed to reduce anxiety (Miskelly, 2005) while enabling such residents to manage their own care at home for a longer time. A smart medication reminder system has been designed that includes a medication reminder function evolving as an assistance tool for improving medication adherence and an electronic health record function that can be used as a communication vehicle to link health professionals with patients and their family members. This system uses information and communication technologies (ICTs) for offering support to those with poor health conditions or physical, sensory, or cognitive difficulties who desire to continue living in their own homes. These patients can use this system to review and send their medication information from their own homes to friends, family, or health and professionals involved in their care.
Despite increases in available home care technology and application, home care delivery can still be improved through advances in human factors, continuous monitoring, cost-effective wearable devices, and reconfigurable systems (Yao et al., 2005). Furthermore, many home care systems are task based rather than ergonomic, which results in limited benefits for the users (Clark & McGee-Lennon, 2011). The aims of this study include the conduction of a face-to-face survey for eliciting the reason for which patients use pill boxes and the presentation of a multiple case study for determining the manner in which the patients use the smart medication reminder system and whether this system effectively improves medication adherence. In addition, we fuse the results of the questionnaires and the case study to provide several suggestions for designing a user-centered reminder system to assist elderly people with chronic conditions in taking medications as prescribed and to improve the quality of their lives.
RELATED LITERATURE Chronic care management is defined as health care management within a health facility for people with one or more chronic conditions or those who are at a high risk of contracting a disease. Chronic problems require continuous, long-term monitoring, rather than episodic assessment. Effective chronic care management generally assists patients in obtaining self-care skills to slow the progression of the disease and includes evidence-based clinical practices, coordinated care across health care settings, ready access to behavioral health services that are integrated with primary care, and the usage of community resources to support patients and families.
Only 5–10% of the elderly with chronic conditions requires care by others. The remaining percentage of patients is self-sufficient with a strong desire to age independently in their own homes (Costa, 1999; McGarry & Schoeni, 2000). Because most elderly residents prefer to achieve this goal for as long as possible, a major objective of elderly care is the facilitation of the ability of elders to maintain and promote their own health care. Home health care is a subset of long-term care and primarily includes skilled nursing delivered in a home setting. This process can be defined as the receipt of assistance or help with at least one activity of daily living (ADL), such as bathing, eating, dressing, walking across a room, and getting in and out of bed, or one instrumental ADL (IADL), such as using a telephone, taking medication, handling money, shopping, and preparing meals. Furthermore, patients staying in their own homes to receive care is both socially and economically beneficial (Miskelly, 2005). A social benefit is that the patients can remain in a familiar environment close to family and friends. Social support has been reported as a strong predictor of elderly depression (Gazmararian et al., 2000; Barefoot et al., 2000). Due to poverty and lack of family support, elderly residents in public elder care homes may be vulnerable to depression, which could increase the likelihood of physical problems such as pain.
In addition, the patient plays an integral role in the management of chronic disease (Bodenheimer et al., 2002). Self- care activities are essential (Arcury et al., 2012) for improving the competence of the elderly in managing their own health conditions independent of institutional care (Hoy et al., 2007). Although the elderly may suffer from chronic diseases, cognitive impairment, and functional limitations, mobilization of their self-care resources can minimize such health problems and enhance their health and well-being (Hoy et al., 2007). By reducing face-to-face consultations and shortening hospital stays, home care technology can help to compensate for inadequacies in health care resources while maintaining or improving care quality (Kun, 2001). Moreover, an increasing number of tools such as websites and smartphone applications have been designed to help individuals to manage their own health care. These achievements in personal health care and tools for such can highlight trends and subtle changes to empower patients and improve patient–doctor communication.
Each elderly patient will ultimately face the challenges associated with memory and cognitive degradation, which may affect their abilities of taking medication as prescribed in addition to self-care management. Therefore, it is important to provide an electronic monitoring system, medication reminders, and medical advice or support to at- home patients. Furthermore, data on medication-taking habits provide important information that enables the doctor to understand the patient’s conditions and to prescribe appropriate medications. Such data may also aid the patients in self-care management and their families and relatives to ensure that the medications are taken as prescribed. Moreover, a reminder system is an important part of remote health care services (Kun, 2001). For people with chronic conditions, such a reminder system and documentation may assist the patient, doctor, friends, and relatives in proper medication consumption. The telephone is the most commonly used tool for providing home reminder services. However, challenges remain in the effective design of a home medication reminder because previous studies have focused on the alarm designs (Watson & Sanderson, 2004). Related studies on home reminder design are few; the recommendations reported in such research is limited to specific users, and parts of the findings may not be widely applied (McGee-Lennon et al., 2011).
This study is focused on the needs of elderly people with chronic conditions who require lifelong treatment for disease management in taking medications as prescribed. First, a questionnaire survey is conducted to determine the reasons why patients repackage their medications into special containers such as pill boxes, for assistance in taking medications. In addition, an experiment is conducted to determine the practicality of a smart medication reminder that includes a medication reminder function evolving as an assistance tool for improving medication adherence and electronic health record functions, which can be used as a communication vehicle to link health care professionals with patients and their family members and friends. This device may maintain long-term records and remained medication parameters of elderly patients remaining at home. Such a system is designed with ICTs in offering support to those who have health conditions or physical, sensory, or cognitive difficulties and wish to continue living in their own homes. The patients can use the reminder to review and send the medication information from their own homes to friends, family, and professionals involved in their care.
METHODS
A face-to-face survey and a multiple case study were conducted to elicit the reasons why elderly people with chronic conditions use pill box, as shown in figure 1 (a), and to determine the effectiveness of the smart medication reminder system, as shown in figure 3-1 (b). Both container designs provide receptacles for a seven-day supply of medication, and each day includes four separate medication compartments.
(a) Standard pill box (b) Smart medication reminder system Figure 1. Containers used for medication storage.
Questionnaire
To elicit the reasons why elderly patients with chronic conditions use or do not use pill boxes and to review their methods for storing medications and taking them as prescribed, a questionnaire was designed for this study to include the following parts: (1) personal and health information, (2) habits of taking the medications, (3) need for assistance in taking the correct dosages of medications at the correct time, and (4) pill box usage. Each part was designed to be analyzed by quantitative and qualitative methods. A five-point Likert scale and a sorting (1, 2, 3) method were used to elicit patients’ agreements in participation and the importance levels of the questions, respectively. Some of the questions were open-ended questions to elicit opinions. Because this study focused on participants older than 65 with chronic medical conditions, one researcher each was assigned to randomly select the participants, conduct the face-to-face survey, and complete the questionnaire for those requiring assistance. The survey participants included 400 elderly people, 147 (36.75%) of which were men and 253 (63.25%) were women.
Experimental design
A one-month preliminary experiment including three paid participants was conducted to test and revise the experimental design. An experiment lasting approximately 45 days was next conducted that included six paid participants older than 65 with chronic conditions requiring lifelong treatment. The participants were offered a smart medication reminder for home use. A pre-experiment questionnaire, mini–mental state examination (MMSE), and application of the Barthel index (Mahoney & Barthel, 1965) were used prior to the experiment to determine the personal and health information of the participants and to measure their ADLs. The entire experiment was then conducted with the reminder system. The participants used the first half month of the experiment period to acquaint themselves with the reminder system. During that time, the researcher addressed any issues in person and immediately. After ensuring that the participants were accustomed to using the smart medication reminder, the following one-month experiment was conducted including two semi-structured questionnaires and a performance measurement to elicit research data for understanding how the patients used the smart medication reminder and whether this device effectively improved prescribed medication adherence.
RESULTS
Survey results The survey participants included 400 elderly patients with chronic medical conditions. 45% of the respondents had on previous occasions forgotten to take their medications. 52.5% of the survey participants used traditional pill boxes. 61.43% were able to take medications as prescribed at home, and 55.71% were able to do so away from home. The reasons stated for using the pill box included that to satisfy their needs of determining whether they took the medications, putting the medications in a safe place, and ensuring that the right medications were taken. The remaining 47.5% of the survey participants did not use the pill box. 63.16% were able to take medications as prescribed at home, and 56.84% were able to do so away from home. The reasons stated for not using the pill box included the lack of desire to change habits and laziness. In addition, such respondents stated that the pill box was not easy to carry, and there was no protection against dampness. However, 32.63% were willing to attempt to use the pill box.
T-test The T-test results indicated a significant difference between males ( = 3.48, σ = 1.59) and females ( = 3.02, σ = 1.55) in the requirement of social support (t = 2.817, p = 0.005).
Chi-square test The results of the chi-square test indicated that care from relatives and friends was the most important factor for the
elderly patients with chronic health conditions ( = 2.31, σ = 0.80), followed by medical information ( = 2.11, σ = 0.68) and social welfare/support information ( = 1.58, σ = 0.79). These test results also indicated that in patients’
requirements for care from relatives and friends care significantly differed among respondents according to education level (x2 = 9.18, p = 0.005), religion (x2 = 30.01, p = 0.013), the number of those suffering from chronic diseases (x2 = 18.01, p = 0.021), medication habits at home (x2 = 17.43, p = 0.008), and medication habits away from home (x2 = 19.41, p = 0.002). The needs of care by relatives and friends for patients whose education levels were elementary, junior high, high school, or college were higher than with master’s degrees. Those under religions of Buddhism, Taoism, Christian, and Catholic had greater needs for care by relatives and friends than those under Yiguandao religion. Whether at home or away, the patients who did or did not take their medication on time or occasionally forget to take their medications had higher needs for care from relatives and friends than those who often forgot to take their medicine. Finally, the patients with four types of chronic medical conditions had lower needs for the care from relatives and friends than other patients.
The chi-square test indicated significant differences in patients’ social welfare/support information needs between genders (x 2 = 13.37, p = 0.001) and among religions (x2 = 24.61, p = 0.008) and medication habits away from home (x2 = 21.33, p = 0.004). The social welfare/support information needs were higher for male patients and those practicing the religions of Yiguandao than those for females and those practicing other religions. Finally, the patients who often forgot to take their medicine away from home had higher social welfare/support information needs than others.
ANOVA Analysis of variance results indicated significant differences among the needs of patients for social resources support, family care, and social service benefits. The least significant difference analysis determined significant difference in patient satisfaction of medication habits at home, those away from home, and family care (p < 0.01). The patients who took their medication on time had higher satisfaction levels with their family care than others. In addition, the patients who often forgot to take their medications comprised the majority requiring social services support, followed by those who took their medications on time, those who did not, and those who occasionally forgot to take their medications. Finally, patients 65–70 years of age had higher needs for social resources support than those 71–90.
Correlation analysis Pearson’s correlation among social resources support, social services support, real-time information, professional health care, and medication satisfaction were analyzed, and the correlation among several factors is shown in figure 4-7. Positive correlations were noted between economic capacity and social resources support (r = 0.503, p < 0.01), economic capacity and social services support (r = 0.375, p < 0.01), economic and real-time information needs (r = 0.298, p < 0.01), and economic and interaction needs regarding medical staff (r = 0.253, p < 0.01). In addition, positive correlations were noted between family relationships and care from family members satisfaction (r = 0.466, p < 0.01) and such relationships and medication satisfaction (r = 0.168, p < 0.01). Finally, negative correlations were noted between economic capacity and medication satisfaction (r = −0.122, p < 0.05), family relationships and social resources support (r = −0.114, p < 0.05), and such relationships and social services support (r = −0.102, p < 0.05).
Experimental results
Six elderly patients participated in the experiment. The MMSE results indicated that three were of normal cognitive status (scores 25–30), and the remaining three were of moderate cognitive impairment (scores 18–22). The results of the Barthel index showed that five participants were independent, and the remaining participant was moderately dependent (score 65) with moderate cognitive impairment. Analysis of the data of the experimental questionnaire by the Wilcoxon rank sum indicated a significant difference in the perceived pressure to take the medication as prescribed among the patients according to cognitive status (p = 0.025). The patients with normal cognitive function agreed that the smart reminder system may reduce such a perception ( = 5), whereas those with moderate cognitive impairment did not agree ( = 2). In addition, analysis of the post-experiment questionnaire showed significant differences in the size of the pill box and the reminder alarm setting among the different cognitive status levels. The patients with normal cognitive function accepted the design size of the experimental pill box (agreement = 2.33, σ
= 0.58) but did not agree that the reminder function was easily set (agreement = 4, σ = 1); rather, their preference was fixed reminder time setting. The experimental results from the pre-experiment, experiment, and post-experiment questionnaires are described in four parts in the following subsections.
Useful functions
The useful functions of the smart reminder system for the participants are described as follows:
1. Auditory stimuli: A reminding design by auditory stimuli such as a ringtone or music (satisfaction = 4.33, σ
= 0.75) or voice ( = 4.17, σ = 0.9) to remind the patient of the medication time and to emit a warning sound to alarm if the time has passed were determined to be useful functions.
2. Visual stimuli: A reminding design by visual stimuli such as a flashing light (satisfaction = 4.83, σ = 0.37) to remind the patient of the medication time in addition to that flashing an hour prior to the time as an early
Equation reproduced from the original PDF.
3. Design assistance: The results of experimental questionnaire showed that after using the reminder system for one month, the average familiarity level of the reminder system was 4.33 (σ = 0.47) and that the mean of the satisfaction with the use of the smart medication reminder system was 4.67 (σ = 0.47). After using the reminder system for one and half months, the results of the post-experiment questionnaire indicated that the mean score of the participants using the system was 85 (0–100, σ = 5). Moreover, three participants cited the helpful design including advance medication reminders, medication loading reminders, and ease of use. These results indicate a high recognition that the smart medication reminder is useful, helpful, acceptable, and satisfactory; however, individual differences remained in the usefulness levels.
4. Medication recorded: The results of the experiment questionnaire showed that the medication recording function was not useful for the participants ( = 2, σ = 0.41). Only one participant required family members to
check the patient’s medication status. Therefore, this participant was satisfied with the medication recording function (satisfaction = 4), but the others were not. In addition, the participants were very satisfied in their interaction with family and friends ( = 4.33, σ = 0.47); the medication recording function was not the main
Equation reproduced from the original PDF.
Unuseful and inadequate functions The unsatisfied and inadequate functions of the smart reminder system for the participants are described as follows:
1. Mobility: The results of the pre-experiment questionnaire showed that half of the participants require medication reminders away from home, and the other half did not. However, after using the smart medication reminder for one month, the results indicated that more participants required the use of the medication reminder away from home ( = 4.83, σ = 0.37). The results of the post-experiment questionnaire showed that
the patients required the medication reminder to have higher mobility ( = 4.5, σ = 0.76) and that they did not like the plug design ( = 4.17, σ = 0.69). Therefore, the medication reminder should be improved for greater
mobility in such components as the medication reminder time and the power cord.
2. Fixed auditory stimuli design: The results of the post-experiment questionnaire showed that the voice reminder was very long (agreement = 3.83, σ = 1.34) and that the warning sound for missed dosage was
very loud (agreement = 3.5, σ = 0.76). These factors were particularly problematic for people living with others.
3. Improper design: The participants did not like the complicated setting process for using the remainder system ( = 4.5, σ = 0.5). In addition, the time setting offers only hourly options ( = 4.3, σ = 0.71), and the participants have to press one button after taking the medication to enable the medication recording function ( = 3.33, σ = 1.49). This design was not accepted by the elderly users.
4. Medication grid design: Two participations had to take 3–4 types of medications at one time, and one had to take the medications before and after eating. Therefore, the medication receptacle size for each day offered only four compartments, which was not useful for these participants.
Infrequently used functions The volume adjustment and redundant design of the medication box for showing breakfast, lunch, dinner, and bedtime on the smart remainder, shown in figure 2, were generally not used by the participants. Only one participant used the functions of recording and medication records. Two participants used early and interval medication reminders. In addition, one participant was willing to allow family members to check their medication information via the Internet; the others did not indicate that the family members should or would check their medication statuses. Furthermore, two participants expressed that they did not need the smart medication reminder to connect with a computer or smartphone, because they did not need such a feature and did not want to spend time to learn how to use it. The other four participants considered the use of such an application if the interface provided functions of voice operation (75%), keyboard (50%), or touch screen (25%).
Figure 2. Redundant design for each day on the medication box.
Figure available in the original PDF paper.
Satisfied functions The results of the pre-experiment questionnaire indicated that the participants are satisfied ( = 3.67, σ = 0.52) with their own methods of remembering to take their medications. Kendall’s W test indicated significant differences in the medication satisfaction levels among pre-experiment ( = 3.67, σ = 0.52), experiment ( = 4.83, σ = 0.41), and post-experiment ( = 4.17, σ = 0.75) responses (p = 0.031) and between pre-experiment and experiment responses (p = 0.02). When the participants used the smart medication reminder, their achievement rate of taking medication as prescribed was 93.5%, and the mean of the improvement in satisfaction was 3.83 (σ = 0.69). The three participants who could take the medication on time were satisfied with the improvement ( = 4, σ = 0.82); the two who occasionally forgot to take their medication were still satisfied with the improvement ( = 3, σ = 0), and the remaining one participant who often forgot to take medications was very satisfied with the improvement (satisfaction = 5).
DISCUSSION
The needs of elderly people with chronic conditions The survey results indicated that approximately 40% of elderly people with chronic medical conditions do not take their medications on time. Moreover, no significant difference was noted in medication status between the patients who did and did not use the pill box. However, 30% of the responders who did not use the traditional pill box were willing to use the new system. The results also showed that the most of the responders needed a reminder system to release their perceived pressure of taking their medications as prescribed. Furthermore, at least 60% of the responders required a tool for reminding them to take their medications as prescribed.
Except for the need for assistance in taking medications, the most important need for the elderly patients was care from family and relatives, followed by medical information and social support or welfare information. Differences in care needs were noted according to the education level, religion, medication habits, and chronic medical conditions of the patients. Those with master’s degrees or Yiguandao beliefs, in addition to those who often forgot to take medication or those with four types of chronic medical conditions, had a lower need for care from relatives. Male patients with Yiguandao beliefs who often forget to take their medications required social support or welfare information and relied on the support from national/community resources to satisfy their home care needs. In addition, the family relationship was an important factor for the patients. The elderly patients with close family relationships showed high medication satisfaction. Those who live with family have higher satisfaction in the care from relatives than those living alone. In addition, whether away from home, patients who were highly satisfied with care from their relatives were able to take their medication as prescribed. Those with close family relationships had lower support needs from national, community, or social networks. Therefore, encouraging elderly patients to pursue a social life and to improve their relationships with relatives and friends is beneficial for their conditions and may even reduce unnecessary expenditures of social resources. The needs of the few elders with independent personalities differed; those patients required care and social support to have satisfactory home care and quality of life.
Finally, economic capacity is an additional important factor for elderly patients. Those with higher economic burdens had lower medication satisfaction and higher needs of social information, social services support, real-time information, and medical assistance. They tended to rely on external support to satisfy their health care needs and tried not to depend on relatives. The 65–70-year-old males preferred to obtain support from national/community/social resources, and the patients who often forgot to take their medications preferred to have more social services support. Therefore, the related organizations should provide elderly patients who are male, have economic burdens, high autonomy, or have satisfactory self-care ability additional assistance for personal health assessment, grant information, and care services.
Needs of smart medication reminder
The survey results indicated that 60% of the responders require a tool for assistance in taking their medications as prescribed. The following experimental results indicate the patients’ needs for the smart mediation reminder:
1. Reminder design: The most important need for the elders is the reminder of the dosage time. The use of auditory stimuli for the main design and visual stimuli for the secondary design are suggested. The auditory stimuli may include a ringtone, music, or voice to remind the patients of medication time, missed dosages, and medication needs. Moreover, the auditory design should avoid using harsh music and the long voice reminders. Also, the smart medication reminder should offer a stop/start button to avoid bothering people who live together. The visual design may use a flashing light for the secondary stimuli to reminding users of the dosage time and include an alert to be activated an hour prior to the dosage time.
2. Mobile medication reminder: The smart mediation reminder should be designed without limitations on time, place, and box size for the needs of the users away from home.
3. Ease of use: The main control button is located on the smart reminder’s lower right side and is marked with a large smile icon for catching the user’s attention. However, the hour-early alarm setting requires that the button be pressed three times. Such an operational design is not easily used by the elderly patients. In addition, the size and location design of the volume adjustment is very small and not easily reached; therefore, the elderly patients tend to not use it. That is, the size and location for the control button design may affect the user’s acceptance. The setting process must avoid the requirement of pressing the same button more than two times. After this process is completed, an auditory function should inform that the setting was successful, and visual stimuli such as a light, icon, or screen information, should be activated as redundant design to assist users with cognitive challenges. Moreover, the elderly patients expected to complete all of the settings through voice operation.
4. Flexible design: The size of medication grid, lengthy voice reminders, and hourly setting are not satisfactory for some users. Moreover, considering that the elderly users may have problems associated with physiological degradation such as hand touch and operation function, a flexible design is suggested.
5. Modular Design: The experimental medication reminder provides multiple functions for satisfying the needs of each user. However, several functions have been deemed unnecessary by the users such as interval medication, recording, medication records, and advance medication reminders. Moreover, despite the participants’ willingness to continue using the medication reminder, it is cost-prohibitive. Hence, a smart medication reminder providing only essential and useful functions is suggested. If the additional functions are offered to consumers at additional prices, the smart medication reminder’s size can be reduced, and its price can be lowered.
Study limitations
The sampling for this study is limited to the Taipei area of Taiwan and outdoor spaces, such as parks, Danshui old streets, and hospitals. Many elderly users were unwilling to fill the questionnaire or to participate in the experiment. Therefore, the responders of this study were more willing to have an independent social life. The participants of the experiment should accept or not reject the use of the new product or the traditional pill box and should be open to either case.
CONCLUSION
In this study, a face-to-face survey and a multiple case study were conducted to elicit the reasons for using or not using a traditional pill box. The results indicated the effectiveness of the smart medication reminder for patients and determined the medication needs of elderly people with chronic medical conditions. This study revealed that 60% patients need a tool for assistance in taking their medication as prescribed. However, the traditional pill box provides only the simple function of storing the medications. The experimental results indicated that the smart medications reminder may effectively assist users in taking their medications as prescribed. Elderly users emphasized their needs of the smart reminder including the ease of use, simple functions, and affordability. However, the smart reminder products currently available are designed with multiple functions such as recording, combined applications, and lack of mobility and flexibility in the design. The gap between the product design and the users’ needs resulted in an unwillingness of consumers to purchase the product.
By using the smart medication reminder, the pressure of taking medications as prescribed may be relieved for the most elderly users. This type of pressure for elderly users with cognitive impairment cannot be reduced because of their need for stronger stimuli of the reminders and additional care by relatives. The essential functions of the smart medication reminder are medication reminders and mobility. The medication recording function was useful for only a few patients who receive the care from family members. Such information should be able to provide information to physicians or related medical staff members. The acceptance of using an electronic/mobile system was low for elderly users, because they are accustomed to telephone communication. Providing voice, keyboard, and touch- screen functions may increase the attraction of the device. In addition, family and social support are important factors to affect the satisfaction of elderly patients in taking medications. Strengthening family and friend relationships and enjoying a social life are suggested for elderly patients. Most of the patients do not want such relationships focusing on their chronic medical conditions. Providing care, social welfare information, and government subsidies for personal healthcare information and services system to the elderly patients with independent personalities and self-care abilities or to male elderly patients with self-care abilities are suggested. Finally, economic, social support, and elder care subsidies are the important factors for patient welfare. The elders with financial pressures require family or government support for a long-term home care system. Further study on the needs of the elderly of various economic levels is suggested for determining the needs of each elderly patient in home care systems, increasing their autonomy to enable them to self-manage their lives, and improve their quality of life.
ACKNOWLEDGMENTS
The authors would like to express their gratitude to National Science Council of Taiwan for the funding under the grant number NSC 101-2221-E-161 -002 -.
REFERENCES
Arcury, T.A., Grzywacz, J.G., Neiberg, R.H., Lang, W., Nguyen, H., Altizer, K. (2012), “Older adults’ self-management of daily symptoms: Complementary therapies, self-care, and medical care”, Journal of Aging and Health, 24(4), 569–597. Barefoot, J.C., Brummett, B.H., Clapp-Channing, N.E. (2000), “Moderators of the effect of social support on depressive
symptoms in cardiac patients”, Am J Cardiology, 86, 438-442. Bodenheimer, T., Lorig, K., Holman, H, (2002), “Grumbach K. Patient self-management of chronic disease in primary care”, JAMA, 288, 2469-2475. Costa, D. (1999), “A house of her own: old age assistance and living arrangements of older nonmarried women”, Journal of
Public Economics, 72, 39-60. Clark, J.S., McGee-Lennon, M.R. (2011), “A stakeholder-centred exploration of the current barriers to the uptake of home care technology in the UK”, Journal of Assistive Technology.
Gazmararian, J., Baker, D., Parker, R., Blazer, D.G. (2000), “A multivariate analysis of actors associated with depression: evaluating the role of health literacy as a potential contributor”, Arch Intern Med, 160, 3307-3314. Hoy, B., Wagner, L., Hall, E.O.C. (2007), “Self-care as a health resource of elders: An integrative review of the concept”,
Scandinavian Journal of Caring Sciences, 21(4), 456–466. Kun, L.G. (2001), “Telehealth and the global health network in the 21st century: from homecare to public health informatics”, Computer Methods and Programs in Biomedicine, 64, 155–67. Mahoney, F.I., Barthel, D. (1965), “Functional evaluation: The Barthel Index”, Maryland State Medical Journal 1965;14:56-61 McGee-Lennon, M.R., Wolters, M.K., McLachlan, R., Brewster, S., Hall, C. (2011), “Name That Tune: Musicons as Reminders
in the Home”, In: Proceedings of ACM CHI 2011, Vancouver, CA. Watson, Sanderson (2004), “Sonification helps eyes-free respiratory monitoring and task time-sharing ” , Human Factors, 46, 497–517. McGarry, K., Schoeni, R. (2000), “Social security, economic growth, and the rise in elderly widows' independence in the twentieth century”, Demography 37, 221-236. Miskelly, F. (2005), “Science and Technology Committee, House of Lords, UK Parliament”, Available from:
http://www.publications.parliament.uk/pa/ld200506/ldselect/ldsctech/20/20we16.htm Steinman, M., Hanlon, J. (2010), “Managing medications in clinically complex elders: There's got to be a happy medium”, JAMA, 304, 1592-1601. Yao, J., Schmitz, R., Warren, S. (2005), “A Wearable Point-of-Care System for Home Use that Incorporates Plug-and-Play and
Wireless Standards”, IEEE Transaction on Information Technology in Biomedicine, 9(3), 363-371.
LISTED IN THE AHFE DIGITAL BOOKSTORE CATALOGUE
Explore the complete digital volume
Advances in Human Aspects of Healthcare
Read this individual research paper free through the original publisher, or explore the full digital proceedings book.
ISBN 978-1-4951-2093-0
Explore this ISBN in the AHFE Bookstore ↗Listed in the July 2026 bookstore catalogue; search by ISBN to confirm current availability · Digital book purchase optional