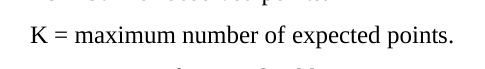This study proposes to evaluate the ergonomic aspects of dental equipments. Based on the requirements proposed by ISO/FDI, on the existing literature and related researches an evaluating system was devised. Thirty nine dental clinics were examined using 165 points-system proposed, distributed in 12 criteria. None of the dental clinics examined showed a bad ergonomics level, 41% were good and 59% reached excellent levels. The point-supported evaluation system proposed is effective in the analysis of the ergonomic conditions of dental equipments, allowing a quantification of their characteristics. Using this system, the dentist can also know the level of ergonomic satisfaction existing in his equipment, and indentify the conditions to be improved. It was concluded that the equipment belonging to dental workplaces evaluated had excellent level of compliance, however corrective measures are needed since even the presence of a few non-conforming items is a sufficient condition to cause injury to users, decreased efficiency and comfort and loss quality of service.
Among the various features of an establishment of dental ergonomic factors are considered decisive to enhance the efficiency, productivity and comfort (Lino, 1972; Eleutério et al., 1985; Barros, 1991; Frazão et al., 1996; Castro and Porto, 1997; Orenha et al, 1998). The effective application of ergonomic criteria enables better mutual adaptation between working environment and employees, creates conditions that contribute to improving quality of service while that enhance the quality of work life, satisfaction and motivation (Rising, et al., 2005).
The development and implementation of checklists have proved an effective method of evaluation in different areas of knowledge. In the area of human resource management the checklists show efficient and effective. Rock [9] proposed a checklist as a method of assigning points to establish the remuneration to different positions in a company. These systems are considered the critical factors and sub-factors to assign levels of importance to the positions so that the score achieved corresponds to a certain level of salary.
The World Health Organization (WHO, 1986) proposed a checklist as a method of quantification of health problems for prioritization of attention. This method assigns weights and values for each criterion and the result of the calculation establishing a list of priority attention to diseases. Guedes (1972) studied the evolution of health status between the administrative regions of São Paulo in the period from 1950 to 1970 used a method of assigning points to quantify the level of priority attention to the disease in each region and thereby establish which regions had higher care needs . Human Aspects of Healthcare (2021) https://openaccess.cms-conferences.org/#/publications/book/978-1-4951-2093-0
In dentistry, the Center for Health Surveillance (SES 1999) developed and applied a scoring system to endorse the hygiene and organization of dental offices. This method is used to determine the level of safety and quality of care that the property offers. This score allows the classification of the property in two (2) categories: high risk (0-70 points) and low risk (71-100 points).
Orenha et al. (1998) evaluated the role of professionals in public dental service and found a need to draw up a checklist that was able to prove with precision and accuracy ergonomic conditions of the rooms of dental care equipment and employees.
Hokwerda et al. (2002 and 2009) conducted a study to assess the posture adopted by dentists in 1250 while performing dental procedures. The authors concluded that the ineffective application of ergonomic requirements, partly by lack of knowledge of professional and part for non-conformity of the equipment they use resulted in high percentages of deviations from the healthy working posture. The authors observed the following ergonomic deficiencies practiced by professionals:
* 89 % have adopted excessive bending the head forward, exceeding the limit considered healthy 20-25 º; * 61 % have adopted rotation combined with a strong neck forward flexion; * 63 % demonstrate trunk flexion exceeding 20 °, considered healthy limit; * 36 % work with the rotated neck combined with a twist of the spine; * 35 % keep their forearms elevated beyond 20 °, considered healthy limit; * 32 % keep their arms at greater than 25 degrees above the horizontal line angle limit considered healthy; * 25 % work with his hands resting improperly; * 47 % did not correctly handle the instruments; * 20 % demonstrate a strong wrist flexion; * 65 % work with stool whose backrest provides incorrect support; * 75 % of working professionals without the patient's head is positioned symmetrically opposite to them, not watching the ergonomic principle that the patient's mouth should be positioned at 40 cm of their eyes, positioned just forward of the line thorax professional, being the professional sitting in an upright, symmetrical and balanced posture ; * 32 % work with feet and legs farther than necessary the dental chair; * 55 % work sitting for more than 7 hours per day; * 75 % work with incorrect lighting and light distribution outside the box.
Another study by Rising et al. (2005) at the University of San Francisco showed that over 70 % of dental students reported pain by the third year of college and this percentage gradually increases from first to fourth year. The authors concluded that the teaching of ergonomics should be better prepared and worked during graduation.
The adoption of poor posture by dentists occurs due to lack of conformity of ergonomic equipment and instruments, whose conception and design need further adaptation to the anatomical and physiological characteristics of the operators. Concomitantly, it appears that the dentist is more concerned with "what” is doing the "how” is doing. The literature shows that recently new concepts for the design of dental equipment were developed based on anatomical and physiological characteristics of the dentist, which are not yet sediment in the manufacturing sector and their design (Hokwerda et al., 2007; Delleman et al., 2004; ISO, 2000). Recent studies reveal high incidence of WRMD for dentists and staff (Leggat et al., 2007). In some regions of Brazil about 30 % of professionals retire prematurely. This has resulted in losses to the health of staff, loss of quality of life and strong financial impact for professionals and for the economy as a whole. Thus, this study aims to develop and implement a checklist able to assess the degree of compliance of ergonomic equipment for employees performing dental care and offer dentists a method that assists in the selection of equipment that allow them to work from healthy way . Additionally, this study provides equipment manufacturers current and useful information so that they can deploy new concepts in the design and manufacture of their products, thereby contributing to the improvement of equipment.
MATERIALS AND METHODS
This study was approved by the Institute of Science and Technology of São José dos Campos - Research Ethics Committee - UNESP process. 11851812.7.0000.0077, according to Resolution 196/96 of the Ministry of Health is a study of the epidemiological, observational, cross-sectional and included equipment belonging to the jobs of 39 Basic Health Units in São José dos Campos / SP.
A scoring system containing 165 ergonomic requirements was developed and implemented, distributed according to Table 1. The evaluation and data collection were performed through videos and photos of 39 places, by an experienced examiner.
Table 1- List of Number of Components and Requirements Evaluated equipment Number of Requirements Dental chair 17 Stool 16 Unit 16 High Speed 12 Low Speed 10 Triple syringe 4 Reflector 21 Auxiliary unit 15 Cabinet 16 Auxiliary table 7 Curing Light 13 Amalgamator 18 Total 165
Each condition was assessed with one of the following criteria:
0 – NON COMPLIANCE. When the estimated requirement is not presented in accordance; 1 - COMPLIANCE. When the estimated requirement presents itself accordingly.
2 - NOT APPLICABLE. When the requirement is not applicable to this specific workplace.
Equation reproduced from the original PDF.
TS = Sum of observed points.
Equation reproduced from the original PDF.
TNA = Sum of not applicable items.
The classification of each studied conditions was performed as described Table 2.
Table 2- Level of satisfaction of ergonomic equipment according to the achieved score Level of satisfaction Percentual
The tabulation of data was performed using Excel proceeding to descriptive statistical analysis with Confidence level set at 95%.
RESULTS AND DISCUSSION
The literature revealed the importance of applying the principles of ergonomics and rationalization of work so as to achieve a perfect fit and harmony of the environment (Porto, 1994; Dias et al., 2007; Hokwerda, 2008; Naressi et al., 2013; Orenha et al., 2013). The ergonomics of the equipment needed to dental care is important to ensure healthy conditions at work and fundamental to achieving high levels of quality and efficiency in the provision of dental care.
Analyzing the results according to local 80% of them had excellent level of satisfaction (Table 3). In 59% of the sites, which equates to 23 health units, we found the level of conformity between 81-90% and 41% of locations, which equates to 16 units, the compliance level were between 71-80% (table 4).
Table 3- Analysis of ergonomic conformity by location Average 80,00 Standard error 0,21 Standard deviation 1,29 Sample variance 1,67 Minimum 74,84 Maximum 80,50 Confidence level (95.0%) 0,42
Table 4- Frequency of sites according to the percentage of conformity % Compliance Rate Frequency %
By another perspective, when analyzing the results against applicable only to items we found high level of conformity, and the average was 90.08% (Table 5).
Analyzing the frequency percentage by class conformity found to 9 items showed compliance level between 0-10%, 5 between 81-90 and 123 between 91-100 % (Table 6). Therefore, the vast majority of applicable items showed high of conformity and few (9 items) with low conformity, suggesting that it is relatively simple to implement corrective measures.
Table 5- Analysis of percentage of conformity per item Human Aspects of Healthcare (2021) https://openaccess.cms-conferences.org/#/publications/book/978-1-4951-2093-0
Table 6- Frequency distribution of the applicable items for class % Compliance N % 0-10 9 6,57 11-20 0 0,00 21-30 0 0,00 31-40 0 0,00 41-50 0 0,00 51-60 0 0,00 61-70 0 0,00 71-80 0 0,00 81-90 5 3,65 91-100 123 89,78 Total 137 100
A critical analysis of 378 items considered nonconforming reveals that they focus on only 27 requirements (Table 7), and 8 of these (Table 7: items 291, 293, 299, 345, 363, 372, 378, 384) are is non-compliant in 39 units.
Figure 1 shows the percentage distribution of the applicable conforming and nonconforming items. Since 166 requirements were evaluated in 39 sites total data evaluated was 6474, with 5343 and 1131 were considered applicable not applicable. Of applicable items, 93% (4965 items) conform and only 7% (378 items) are not compliant.
The scoring system used for classification of dental care rooms proved to be efficient in the general housing conditions. The differences in equipment belonging to each site were represented numerically and level of ergonomic satisfaction was evaluated efficiently.
In most places there was a predominance of a standard type of equipment which carries little difference between the levels of conformity among the analyzed workplaces. In much of the equipment, some characteristics that contribute to harmony and aesthetic balance were not present. The aforementioned factors are responsible for the perception of quality of care for the patient, according to Castro (1997).
Table 7- Percentage of non-compliance in accordance with the items.
Figure 1- Distribution of applicable items to the Nonconforming item detail
Although few items do not comply and the percentage of compliance is high, corrective measures are needed since only one item not as it has potential to cause harm to the health of the operator and loss of quality of service.
It is observed that most of the non-conforming items are the responsibility of the equipment manufacturer and only the item 384 is responsible for the competence of jobs. This shows that it is for service managers to establish, in the bidding for the acquisition of equipment, ergonomic criteria as mandatory requirements process (Silva et al., 2011).
Likewise, manufacturers must develop and market equipment that meet ergonomic, requirements compatible with the anatomical and physiological characteristics of their users by providing them with healthy working conditions. Ergonomic requirements cannot be considered as accessories or luxury items being offered only on more sophisticated equipment, but a minimum quality requirement therefore essential in all types of equipment.
CONCLUSION
The ergonomic analysis of the equipment revealed that there is a good or excellent level of compliance, however corrective measures are necessary since the presence of a few non-conforming items is enough to cause injuries to users, reduced efficiency and comfort and quality loss condition service.
REFERENCES
Barros, O.B. (1991). Ergonomia 3 – Ambiente físico de trabalho, a produtividade e a qualidade de vida em odontologia. Lins: Garagem, 286p. Castro, J. R. F., Porto, F. A. (1977) Organização do trabalho para execução de restauração de amálgama: operador
com e sem auxiliar odontológica. Rev. Gaúcha Odontol., v. 25, p.4. Eleutério, D. et al. (1985). Adequação do consultório para trabalho com pessoal auxiliar: equipamento necessário para colocar paciente deitado e trabalhar a quatro mãos. Cap. VI (Parte II). Odontol. Mod., v.12, p.42-54. Frazão, P. et al. (1996). Ambientes de trabalho odontológico na perspectiva do Sistema Único de Saúde. Franca:
EPATESPO. Lino, H. L. (1972). Estudos de tempos operacionais na utilização de equipamentos odontológicos convencionais e simplificado. Londrina, 84p. Tese (Doutorado) - Universidade Estadual de Londrina. Orenha, E. S; Eleuterio, D., Saliba, N. A. (1998). Organização do atendimento odontológico no serviço público:
trabalho auxiliado, produtividade e ambiente físico. Rev. Odontol., v.27, p.215 – 24. Rising Dwb, Bennett Bc, Hursh K, Plesh O. (2005). Reports of body pain in a dental student population. J Am. Dent Assoc. 136(1):81-6. Rock, M. L. (1992), Administração da remuneração. In: WERTHIER, W.B.J., DAVIS, K. Administração do pessoal
e recursos humanos. 2. ed. São Paulo: Makron Books. cap. 14, p. 319-45. Organização Mundial De Saúde. (1986). Identificação dos problemas prioritários de saúde: material sobre o enfoque de risco na atenção materno-infantil, p. 25-44. Guedes, J.S. (1972). Contribuição para o estudo da evolução do nível de saúde do Estado de São Paulo: análise das
regiões administrativas. 1950-1970. São Paulo. Tese (Doutorado) - Faculdade de Odontologia, Universidade de São Paulo. Secretaria De Estado Da Saúde (SES). (1999). Centro de Vigilância Sanitária. Resolução SS-15. Hokwerda O. (2002). Eindrapportage Sonde project. Nieuwegein: Movir. Hokwerda O, Ruijter R, Shaw S. (2009). Adopting a healthy sitting working posture during patient treatment.
Groningen: University Medical Center Groningen. Rising, D.W.B; Bennett, B.C.; Hursh, K; Plesh, O. (2005). Reports of body pain in a dental student population. J Am. Dent Assoc., 136(1):81-6. Hokwerda, O; Wouters, J.A.J; de Ruijter, R.A.G; Zijlstra-Shaw, S. (2007). Ergonomic requirements for dental
equipment: guidelines and recommendations for designing, constructing and selecting dental equipment. [S.l]: European Society of Dental Ergonomics; 2007 [accessed in 29 mar. 2012]. Available at: http://www.optergo.com/images/Ergonomic_req_april2007.pdf. Delleman, N.J.; Haslegrave, C.M.; Chaffin, D.B. (2004). Working postures and movements: tools for evaluation and engineering. Boca Raton: CRC.
INTERNATIONAL ORGANIZATION FOR STANDARDIZATION. ISO 11226:2000. (2000). Ergonomics: evaluation of static working postures. Geneva: ISO. Leggat, P.A.; Kedjarune U, Smith Dr. (2007). Occupational health problems in modern dentistry: a review. Ind
Health.; 45(5):611-21. Porto, F.A. (1994). O consultório odontológico. São Carlos: Scriptti, 152p. Hokwerda, O. (2008). Vision of the future of ergonomics in dentistry. Nederlands tijdschrift voor tandheelkunde 115, p. 429-34. Naressi, W. G., Naressi, S. C. M., Orenha, E. S. (2013). Ergonomia e Biossegurança em Odontologia. São Paulo-
SP: Artes Médicas, v.1. p.128. Orenha, E. S., Yui, K. C. K., Lencioni, C. S. B., Torres, C. R. G. (2013). Princípios de Ergonomia Aplicados ao Atendimento Odontológico In: Odontologia Restauradora. Estética e Funcional. Princípios para a prática clínica..1 ed. São Paulo-SP: Livraria Santos Editora LTDA., v.1, p. 47-82. Dias, M.C.; Sundefeld, M. L. M. M., Orenha, E. S. (2007). Avaliação ergonômica dos equipamentos presentes nos
estabelecimentos de assistência odontológica pertencentes à cidade de Araçatuba-SP. Revista do Instituto de Ciências da Saúde (UNIP). , v.25, p.307 - 311. Silva, J. C. P., Bormio, M.F., Orenha, E. S. (2011). O emprego da metodologia EWA em uma análise ergonômica de um consultório odontológico. In: Metodologia em design: inter-relações. 1 ed. São Paulo: Estação das Letras e Cores., v.1, p. 345-359.
LISTED IN THE AHFE DIGITAL BOOKSTORE CATALOGUE
Explore the complete digital volume
Advances in Human Aspects of Healthcare
Read this individual research paper free through the original publisher, or explore the full digital proceedings book.
ISBN 978-1-4951-2093-0
Explore this ISBN in the AHFE Bookstore ↗Listed in the July 2026 bookstore catalogue; search by ISBN to confirm current availability · Digital book purchase optional