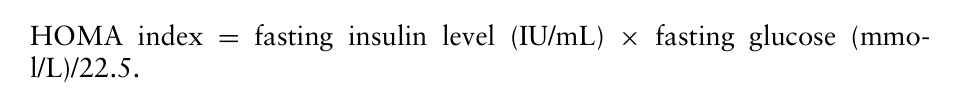Irina Kurnikova, Ramchandra Sargar, Alexi Pavlov, Zhanar Baisenbaeva, Natalia Zabrodina, Maria Zavalina (2023). Quantitative assessments in evaluating the effectiveness of arterial hypertension treatment: new technologies. In: Human Interaction and Emerging Technologies (IHIET-AI 2023): Artificial Intelligence and Future Applications. AHFE Open Access, vol. 70, pp. 327–333. https://doi.org/10.54941/ahfe1002959
1 Department of Therapy and Endocrinology, RUDN University, Miklukho-Maklayast. 6 117198 Moscow, Russia; Department of Aviation and Space Medicine, Federal State Budgetary Educational Institution of Further Professional Education, Russian Medical Academy of Continuous Professional Education, Barrikadnaya., h.2/1, b.1125993 Moscow, Russia ↗
2 Department of Therapy and Endocrinology, RUDN University, Miklukho-Maklayast. 6 117198 Moscow, Russia ↗
3 Department of Aviation and Space Medicine, Federal State Budgetary Educational, Institution of Further Professional Education, Russian Medical Academy of Continuous Professional Education, Barrikadnaya., h.2/1, b.1125993 Moscow, Russia ↗
Background. In the practice of clinical research, it is traditionally accepted to evaluate parameters that characterize the degree of impairment or loss of the function of an organ or system, and not their preservation. A fundamental change in the approach distinguishes a new trend in modern medicine, which makes it possible to assess the degree of preservation of functional resources, which was the basis of this study.Study purpose: To develop a method for dynamic quantitative assessment of the severity of arterial hypertension and evaluate the relationship between a qualitative indicator of arterial hypertension and a quantitative indicator.Instruments and Data Collection Procedure. Index of adaptive aptitude (IAA) (patent for invention No. 2342900 "Method for eavaluation of the functional reserves of the body", author - Kurnikova I. A.). using automated assessment (certificates of official registration No. 2007614560 and No. 2007613898).IAA=0.011(P-P*)+0.014(S-S*)+0.008(D-D*)+0.009(W-W*),Where: P - actual heart rate (b/min.); P* - ideal pulse rate (beats/ min.); S - systolic blood pressure, actual average per day (mm Hg); S* – ideal systolic blood pressure (mm Hg); D - diastolic blood pressure, actual average per day (mm Hg); D* - ideal diastolic blood pressure (mm/Hg); W - body weight at the time of examination (kg); W* - ideal body weight (kg); H - patient's height at the time of examination (cm).Assessment of daily heart rate variability on the Valenta system, equipped with a program for computer processing of spectral analysis indicators.Results:- 143 patients with arterial hypertension (AH) were examined. The relationship between a qualitative indicator - the severity of AH and quantitative indicators - rehabilitation potential, the numerical value of which is PAS, the circadian index (CI) as an indicator of increased sensitivity of the heart rate to sympathetic stimulation, and the LF/HF vago sympathetic balance coefficient, which increases with hypersympathatic tone, was considered. Statistical analysis of the surface plot using the weighted least squares distance allowed this relationship to be clearly demonstrated. Quantitative analogue of the Framingham arterial hypertension severity scale (AHSS) in a specific patient (certificate for invention №. 201152181)AHSS = 119,31 + 2,22× (CI) - 2,03× (IAA) - 1,33×(2×(CI)) + 2,72×(CI)× (IAA) + 7,06×(IAA)where: AHSS less than 120 - normal. Mild AHSS = 121 – 130 points; average severity of AHSS = 131 – 140 points; severe AHSS - 141 points or more. The effectiveness of rehabilitation is good with AHSS less than 120, satisfactory - with 121 - 130; unsatisfactory - more than 131.For illustration, the data of 54 patients are presented. Observation group "1" - patients with AH (BMI<25), mean age - 49±1.9 years (19 people). Observation group "2" - patients with metabolic syndrome (BMI>25; HOMA index> 2.5), mean age - 50±1.7 (35 people). All patients were assessed for the severity of hypertension according to the WHO criteria and the AHSS index at the beginning of the study. Normal value was achieved in 41.8% in 1st group during treatment, in 47.1% there was a decrease in the severity of AH according to AHSS. In group 2, in patients with metabolic syndrome during treatment, it was possible to normalize blood pressure in 55.8%, and to obtain satisfactory results in 35.9%.Conclusion. Developed mathematical modeling methods, a quantitative analogue indicator of the severity of arterial hypertension - AHSS allows you to dynamically monitor the effectiveness of treatment and evaluate the achieved result based on a quantitative assessment within the severity indicated by the classification. The effectiveness of the rehabilitation of patients with hypertension is considered sufficient if the AHSS decreases below the value of 120 units or one level from the baseline
Arterial hypertension (AH) is a major factor in premature death and disabi- lity in all countries of the world (Franklin et al., 2009; Williams et al., 2018). It is associated with the development of cardiovascular diseases, heart failure and kidney disease. AH is often associated with diabetes mellitus, which is identified as a concomitant risk factor (Cosentino et al., 2019; Izzo et al., 2013). The modern classification of hypertension includes distribution by severity, stage, target organ damage and the development of associated cli- nical conditions. There is a specific procedure for measuring blood pressure (BP) to determine the stage and other components of the diagnosis (Ward et al., 2012; Albasri et al., 2017). The greatest difficulty, in our opinion, is the diagnosis of the severity of hypertension in untreated patients (Task et al., 2016; Thomopoulos et al., 2017). This is quite convenient at the stage of primary diagnosis, but subsequently, against the background of ongoing therapy and constant medication, it is very difficult to obtain an objective
result. Even in the process of adequate therapy, changes in individual para- meters of the body and lifestyle, the severity in the diagnosis still corresponds to that established during the initial diagnosis, so the “severity” indicator cannot be used in the dynamic assessment of the progression of the disease or the effectiveness of the treatment of hypertension.
But control is very important, since the ongoing therapy, today, is a com- plex of drugs with different mechanisms of action, and is also prescribed to a patient with comorbid pathology (most often a combination of hyper- tension and type 2 diabetes). Consequently, there is a risk of polypharmacy, which means not only positive effects from the therapy, but also negative ones. The current situation requires the search for new methods of evalua- tion. The most promising methods seem to us to allow assessing the state of the cardiovascular system at the level of the whole organism (assessment of the state of regulatory mechanisms, primarily autonomic regulation and adaptation) for a certain period of time (daily monitoring of blood pressure) taking into account the individual characteristics of the organism.
From the point of view of physiology, the human body, as a dynamic system, experiences constant stress under modern conditions, to which it con- tinuously adapts by changing the functioning of individual systems and the tension of regulatory mechanisms. The reaction of the body depends not only on the strength and time of exposure, but also on the availability of functi- onal internal resources. In response to the impact of stress factors, a general adaptation syndrome is formed (Selye G, 1960). The degree of tension of regulatory systems is determined by the tone of the autonomic nervous system and affects the level of functioning of blood circulation, mobilizing functional reserves. The autonomic nervous system plays the main regulatory role in the life of the body. Control of the constancy of the internal environment is the most important function of the ANS, because blood pH, ion concentration, blood pressure, body temperature, heart rate, blood sugar, etc. determined by the functional state of the autonomic nervous system. On the other hand, the ANS (above segmental divisions) provides various forms of physical and mental activity of a person. HRV assessment is based on the concept of the cardiovascular system as a universal indicator of the body’s adaptive capabili- ties (Lehtonen et al., 2016). The closest and most understandable approach to the analysis of HRV for physiologists and clinicians is based on the concepts of the mechanisms of neuro hormonal regulation (Baevsky, 2014; Mantano et al., 1994; European Society, 1996).
STUDY PURPOSE: To develop a method for dynamic quantitative asses- sment of the severity of arterial hypertension and evaluate the relationship between a qualitative indicator (severity I, II, III) of arterial hypertension and a quantitative indicator.
DESIGN 143 people were examined. At the beginning of the study, all patients had no compensation for arterial hypertension (amlodipine), despite the fact that 100% of patients received antihypertensive therapy.
Quantitative Assessments in Evaluating the Effectiveness 329
Two observation groups and 1 comparison group were formed. Observa- tion group “1” - patients with AH (BMI<25), mean age - 49±1.9 years (19 people). Observation group “2” - patients with metabolic syndrome (BMI>25; HOMA index> 2.5), mean age - 50±1.7 (35 people). Compari- son group (Group 3) - 66 patients with type 2 diabetes, conditionally divided into three subgroups: “3a”- patients with type 2 diabetes with AH cBMI<25; HOMA index<2.5 (15 people), mean age - 54±1.3 years; “3b”- patients with type 2 diabetes with AH with BMI>25; HOMA index>2.5 (44 people), mean age - 52±0.6 years; “3c” - patients with type 2 diabetes without cardiova- scular pathology with BMI>25; HOMA index>2.5 (7 people), mean age - 51±1.8 years. Dyslipidemia was noted at the beginning of the study in all patients with metabolic syndrome and diabetes mellitus.
The diagnosis of arterial hypertension was made in accordance with clini- cal guidelines. The diagnosis of stable angina was based on the criteria set out in the European Society of Cardiology Guidelines for Stable Angina, taking into account and integrating clinical and functional examination methods.
The study was conducted at the clinical base of RUDN University – at the Central Clinical Hospital of Civil Aviation (Moscow) and “Heart Center Shymkent”(Shymkent, Kazakhstan). The conclusion of the Ethics Committee of the Medical Institute of the RUDN University (Moscow, Russia) - Protocol №. 9, March 17, 2016.
INSTRUMENTS AND DATA COLLECTION PROCEDURE Method of Investigation: In a blood plasma sample taken on an empty stomach, the lipid spectrum was determined by the level of total choleste- rol (CH), triglycerides (TG), high-density lipoprotein (HDL), low-density lipoprotein (LDL), very-low-density lipoprotein (VLDL), atherogenic index according to the formula : AI \u003d (total cholesterol - HDL cholesterol) / HDL cholesterol. The control of carbohydrate metabolism was provided by the study of the glycemic profile. Compensation criteria for diabetes and the risk of developing late complications of type 2 diabetes mellitus were determined according to the European Diabetes Policy Group criteria [1999]. Insulin, C-peptide was determined by the method of monoclonal antibodies and HbA1c by immunoturbodimetry. Insulin resistance was determined by the formula:
Equation reproduced from the original PDF.
Index of adaptive aptitude (IAA) (patent for invention No. 2342900 “Method for eavaluation of the functional reserves of the body”, author - Kurnikova I. A.). using automated assessment (certificates of official registration No. 2007614560 and No. 2007613898).
IAA = 0.011(P-P*)+0.014(S-S*)+0.008(D-D*)+0.009(W-W*) Where: P - actual heart rate (b/min.); P* - ideal pulse rate (beats/ min.); S - systolic blood pressure, actual average per day (mm Hg); S* – ideal systolic blood pressure (mm Hg); D - diastolic blood pressure, actual average per day
Table 1. Low OR and the risk of developing cardiovascular disease (group 1).
(mm Hg); D* - ideal diastolic blood pressure (mm/Hg); W - body weight at the time of examination (kg); W* - ideal body weight (kg); H - patient’s height at the time of examination (cm).
The IAA level corresponded to the basic (biological) component of the reh- abilitation potential (Kurnikova et al., 2020). Rehabilitation potential (RP): “-”values - rehabilitation potential is high; 0 - 0.3 - rehabilitation potential is satisfactory; > 0.3 - rehabilitation potential is low. Assessment of daily heart rate variability on the Valenta system equipped with a program for computer processing of spectral analysis indicators: TF, HF, LF, VLF, ULF, LF / HF, HF (%), LF (%), VLF (%), ULF (%), CI and time analysis indicators: SDNN, SDANN, pNN50.
Methods of statistical processing of research results. Statistical processing of the obtained data was carried out using the STATISTICA software package (StatSoftInc. version 6.0, USA). Qualitative variables are presented as abso- lute and relative frequencies of occurrence (%). Quantitative variables in 2 independent groups were compared with a normal type of distribution using the ANOVA analysis of variance. Significance of differences between inde- pendent groups in terms of qualitative characteristics - by a non-parametric method using a two-sided Fisher’s exact test. The level of statistical signifi- cance was taken as p<0.05. The relative risk (RR) and odds ratio (OR) were calculated using the Wolf formula, while stratifying risks for cross-sectional and cohort studies.
RESULTS
In assessing the relative risk and odds ratio in the group of patients with hypertension without obesity, it was noted that low rehabilitation potential does not affect the relative risk of severe hypertension (RR = 1.05) and coro- nary artery disease (RR = 0.57), because the severity of the disease is already quite high. There was an increase in the relative risk of developing myocardial infarction and stroke in patients of this group (RR = 1.71), and the relative risk of the likelihood of CHF is even higher (RR = 2.67) (Table 1).
Patients with metabolic syndrome and low rehabilitation potential have a high relative risk of stroke (RR = 2.36), and in the prospective aspect, a high odds ratio for developing CHF (OR = 6.0) was noted (Table 2).
In the group of patients with type 2 diabetes and normal body weight with AH (group 3a) and in the group of obese patients with AH (group 3b), low rehabilitation potential prevailed, so it was incorrect to calculate the risk at this stage of the pathology.
Quantitative Assessments in Evaluating the Effectiveness 331
Table 2. Low OR and the risk of developing cardiovascular disease (group 2).
In patients with arterial hypertension, a relationship was found suggesting an increase in the severity of hypertension with a low rehabilitation potential. At the stages of carbohydrate metabolism disorders, a relationship was found between a decrease in the rehabilitation potential with an increase in the level of glucose, triglycerides and IC.
The relationship between a qualitative indicator - the severity of AH and quantitative indicators - rehabilitation potential, the numerical value of which is IAA, the circadian index (CI) as an indicator of increased sensitivity of the heart rate to sympathetic stimulation, and the LF/HF vago sympathetic balance coefficient, which increases with hypersympathatic tone, was consi- dered. Statistical analysis of the surface plot using the weighted least squares distance allowed this relationship to be clearly demonstrated. Quantitative analogue of the Framingham arterial hypertension severity scale (AHSS) in a specific patient (certificate for invention №. 201152181): AHSS = 119,31 + 2,22× (CI) - 2,03× (IAA) - 1,33×(2×(CI)) + 2,72×(CI)× (IAA) + 7,06×(IAA)
Where: AHSS- arterial hypertension severity scale; CI- the circadian index; IAA- Index of adaptive aptitude.
Criteria for evaluation: AHSS less than 120 - normal. Mild AHSS = 121 – 130 points; average severity of AHSS = 131 – 140 points; severe AHSS - 141 points or more. The effectiveness of rehabilitation is good with AHSS less than 120, satisfactory - with 121 - 130; unsatisfactory - more than 131.
For illustration, the data of 54 patients are presented. Observation group “1” - patients with AH (BMI<25), mean age - 49±1.9 years (19 peo- ple). Observation group “2” - patients with metabolic syndrome (BMI>25; HOMA index> 2.5), mean age - 50±1.7 (35 people). All patients were assessed for the severity of hypertension according to the WHO criteria and the AHSS index at the beginning of the study. The study was repe- ated against the background of antihypertensive therapy according to the STAG criterion (the severity according to the WHO criteria did not change) (Table 3).
Normal value was achieved in 41.8% in 1stgroup during treatment, in 47.1% there was a decrease in the severity of AH according to AHSS. In group 2, in patients with metabolic syndrome during treatment, it was possi- ble to normalize blood pressure in 55.8%, and to obtain satisfactory results in 35.9%.
Table 3. Assessment of the degree of effectiveness of antihypertensive therapy according to the AHSS criterion.
Table available in the original PDF paper.
Severity of arterial hypertension
Clinical group Normal 1 degree 2 degree 3 degree group 1 1 study 2 study 0 (0 %) 7 (41,1%) 2 (11,8 %) 8 (47,1 %) 11 (64,7 %) 2 (11,8 %) 4 (23,5 %) 0 (0 %)
group 2 1 study 2 study 0 (0 %) 19 (55,8%) 4 (11,8 %) 12 (35,9 %) 15 (44,1 %) 3 (8,8 %) 15 (44,1 %) 0 (0 %) Notes: 1 study - date of observation; Study 2 – 3 months after therapy optimization.
CONCLUSION
Developed mathematical modeling methods, a quantitative analogue indica- tor of the severity of arterial hypertension - AHSS allows you to dynamically monitor the effectiveness of treatment and evaluate the achieved result based on a quantitative assessment within the severity indicated by the classifica- tion. The effectiveness of the rehabilitation of patients with hypertension is considered sufficient if the AHSS decreases below the value of 120 units or one level from the baseline
REFERENCES
Albasri A. et al. A comparison of blood pressure in community pharmacies with ambulatory, home and general practitioner office readings: systematic review and meta-analysis //Journal of hypertension. - 2017. - T. 35. - N. 10. - C. 1919. Baevsky R.M. Forecasting states on the verge of norm and pathology / R.M.
Baevsky – M., 2014. – 295 c. Cosentino F, Grant P, Aboyans V et al. 2019 ESC Guidelines on diabetes, pre-diabetes, and cardiovascular diseases developed in collaboration with the EASD: The Task Force for diabetes, pre-diabetes, and cardiovascular diseases of the European Soci- ety of Cardiology (ESC) and the European Association for the Study of Diabetes (EASD). Eur Heart J 2019, published online on 31 August 2019. Franklin SS, Lopez VA, Wong ND, et al. Single versus combined blood pressure
components and risk for cardiovascular disease: the Framingham Heart Study. Circulation 2009; 119: 243–250. 21. Izzo R, de Simone G, Trimarco V. et al. Hypertensive target organ damage predicts incident diabetes mellitus. EurHeartJ. epub 27 June 2013. Kurnikova, I., Buturlina, S., Sargar, R., Zabrodina, N., Yurovsky, A.Information-
Analytical Systems for Assessing the Rehabilitation of the Patients with Endocrine Diseases. Advances in Intelligent Systems and Computing, 2020, 1205 AISC, pp. 115–121. Lehtonen AO, Puukka P, Varis J et al. Prevalence and prognosis of ECG abnormalities in normotensive and hypertensive individuals. J Hypertens 2016; 34: 959–966. Mantano N, GnecchiRuscone T, Porta A, Lombardi F, Pagani M, Malliani A (1994)
Power spectrum analysis of heart rate variability to assess the changes in sympa- thovagal balance durcin graded ortzhostatic tilt. Circulation 90: 1826–1831;
Quantitative Assessments in Evaluating the Effectiveness 333
Task FM, Hoes AW, Agewall S et al. 2016 European Guidelines on cardiovascular disease prevention in clinical practice: The Sixth Joint Task Force of the European Society of Cardiology and Other Societies on Cardiovascular Disease Prevention in Clinical Practice (constituted by representatives of 10 societies and by invi- ted experts) Developed with the special contribution of the European Association for Cardiovascular Prevention & Rehabilitation (EACPR).EurHeart J 2016; 37: 2315–2381. Task Force of the European Society of Cardiology and the North American Society of
Pacing and Electrophysiology. Heart Rate Variability. Standards of Measurement, Physiological Interpretation and Clinical Use, 1996. Thomopoulos C, Parati G, Zanchetti A. Effects in individuals with high-normal and normal blood pressure: overview and meta-analyses of randomized trials. J Hypertens 2017; 35: 2150–2160. Ward AM, Takahashi O, Stevens R, Heneghan C. Home measurement of blood
pressure and cardiovascular disease: systematic review and meta-analysis of prospective studies. J Hypertens 2012; 30: 449–456. Williams B, Mancia G, Spiering W et al. 2018 ESC/ESH Guidelines for the management of arterial hypertension: The Task Force for the management of arterial hypertension of the European Society of Cardiology and the European Society of Hypertension: The Task Force for the management of arterial hypertension of the European Society of Cardiology and the European Society of Hypertension. JHypertens 2018; 36(10): 1953–2041.
LISTED IN THE AHFE DIGITAL BOOKSTORE CATALOGUE
Explore the complete digital volume
Human Interaction and Emerging Technologies (IHIET-AI 2023): Artificial Intelligence and Future Applications
Read this individual research paper free through the original publisher, or explore the full digital proceedings book.
ISBN 978-1-958651-46-9
Explore this ISBN in the AHFE Bookstore ↗Listed in the July 2026 bookstore catalogue; search by ISBN to confirm current availability · Digital book purchase optional